

1. Define the pricing decision
The transaction question is how much enterprise value is supported after a clinical AI product has completed a trial or prospective evaluation. A positive readout can remove uncertainty, create new uncertainty or do both. The result may establish performance for one version, site, population, workflow and comparator while leaving adoption, reimbursement, scalability and cash conversion unresolved.
The buyer should define the intended use before selecting a valuation method. It should identify the clinical condition, target population, user, setting, input data, model output, required action and consequence of error. A triage tool that changes worklist priority differs from autonomous diagnosis, documentation support or treatment recommendation. The evidence and liability perimeter follow the actual use.
The acquisition thesis should be expressed as a testable chain. An eligible patient reaches the pathway; usable data enter the validated system; the correct model version produces an output; the intended clinician receives and understands it; care changes appropriately; the service has capacity to act; patient or system outcomes improve; an authorised buyer pays; and cash is collected after deployment, support, monitoring and compliance costs.
Value should be separated into collected stand-alone contribution, protected continuity, funded improvement, buyer-specific synergy and unproven option value. Regulatory authorisation, a journal publication or a successful hospital pilot can support specific links. None should automatically move the entire platform into the central valuation case.
2. Build an evidence ladder
Clinical AI evidence matures through distinct questions. Technical verification asks whether software and data pipelines operate as specified. Analytical validation tests whether outputs agree with an appropriate reference. Clinical validation evaluates association with the clinical condition or state. Prospective clinical utility tests whether using the output changes decisions, care or outcomes in practice.
Implementation evidence asks whether the product works in the operating system around it. Adoption, turnaround time, overrides, alert burden, training, downtime, equity, capacity and exception handling can determine realised value. Health-economic evidence then compares the full pathway with current care. Reimbursement evidence identifies who is authorised and willing to pay, for what unit, under which conditions.
Post-market evidence completes the ladder. A model can degrade through population change, device replacement, coding practice, protocol change or software update. The FDA's lifecycle guidance and international good machine-learning-practice principles emphasise risk management throughout the total product life cycle.[1][8] Value depends on the ability to detect and manage change rather than on a frozen accuracy result.
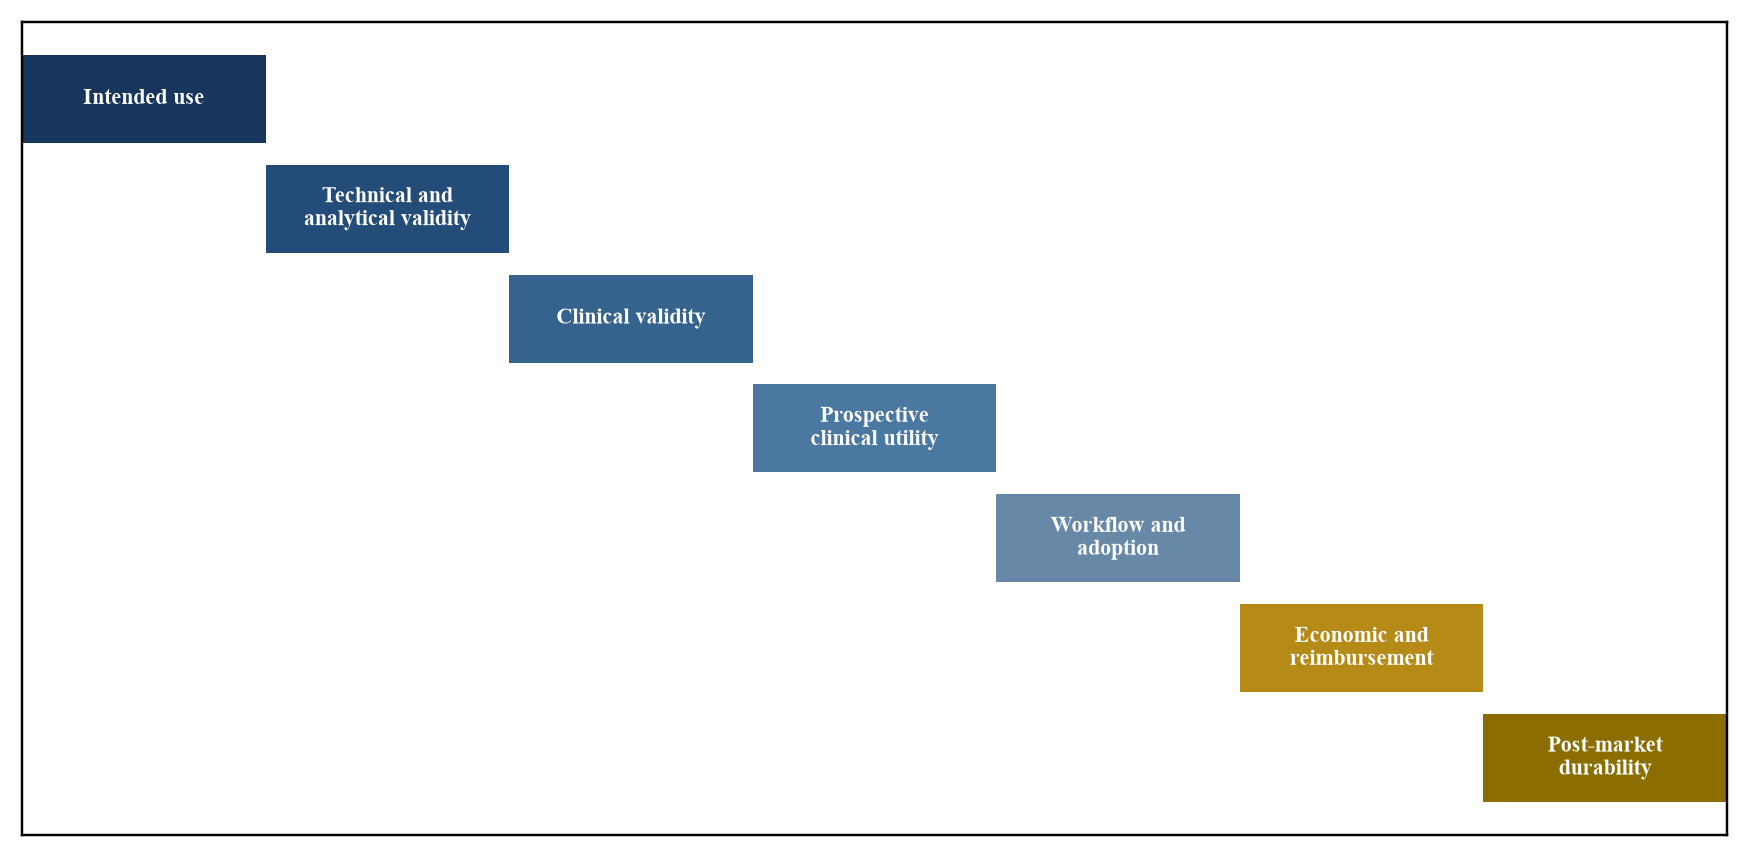
Each layer supports a distinct decision; evidence at a higher layer does not cure a missing lower-layer control.
| Evidence layer | Core question | Decision supported | Valuation consequence |
|---|---|---|---|
| intended use | what decision, user and population? | product perimeter | defines addressable evidence |
| analytical validity | does output match a reference? | technical performance | supports development asset |
| clinical validity | does output relate to condition? | clinical association | supports regulated claim |
| prospective utility | does use improve decisions or outcomes? | adoption and purchasing | supports probability-weighted revenue |
| implementation | can sites operate it reliably? | scale readiness | supports deployment margin |
| economics and payment | who benefits and who pays? | coverage and budget | supports collected cash flow |
| post-market durability | does value persist after change? | terminal economics | supports duration and multiple |
Proposed framework; the required evidence depends on intended use, risk, setting and jurisdiction.
3. Reconstruct the prospective study
The buyer should reconstruct the study from protocol to analysis rather than relying on the abstract or headline endpoint. It should identify registration, protocol version, statistical analysis plan, amendments, sites, enrolment, inclusion and exclusion criteria, comparator, sample-size assumptions, missing-data handling and stopping rules. Prospective registration and reporting frameworks such as SPIRIT-AI, CONSORT-AI and DECIDE-AI improve transparency but do not replace diligence.[32][33][34]
The model version is part of the tested intervention. The buyer should identify weights, thresholds, preprocessing, input devices, software dependencies and user interface. Any difference between the evaluated and commercial versions should be mapped to verification, validation and regulatory assessment. A product described by brand name can contain materially different clinical systems over time.
Site selection can create optimistic performance. Academic centres may have specialist staff, higher-quality data and implementation support unavailable to community sites. The team should compare trial sites with the addressable market across prevalence, demographics, devices, workflows, staffing and care pathways. Excluded or failed cases belong in the economic population.
The comparator should represent actual care. A historical comparator can be affected by secular trends, coding, staffing or protocol changes. A silent deployment tests model performance without measuring behavioural response. A randomised workflow study can identify causal impact more strongly, but contamination, clinician learning and site effects still require analysis.
| Dimension | Evidence | Failure signal | Price response |
|---|---|---|---|
| protocol | registered plan and amendments | endpoint or population changed after data | reduce certainty and test sensitivity |
| model version | reproducible artefact and configuration | commercial version differs | exclude unsupported benefit |
| population | inclusion, exclusion and missing cases | narrow or selected cohort | cap addressable population |
| comparator | contemporaneous care pathway | weak or shifting baseline | lower causal confidence |
| sites | representative operating settings | expert-site dependence | price deployment cost and delay |
| analysis | prespecified methods and uncertainty | selective subgroup emphasis | use conservative central case |
Proposed diligence catalogue; clinical and statistical specialists should determine materiality.
4. Read endpoints through the care pathway
Accuracy, sensitivity, specificity, area under a curve and calibration describe model behaviour under a defined population. Their economic meaning depends on prevalence, threshold, workflow and consequence. A small improvement in discrimination can have limited value when the operating point creates many false positives or when clinicians cannot act on the result.
The buyer should convert endpoints into a patient and work queue. True positives, false positives, false negatives and true negatives should be shown for the intended population. Each category can create investigation, treatment, delay, anxiety, harm, capacity use and cost. Confidence intervals and subgroup results should remain visible.
Process endpoints can be valuable when they connect to capacity or outcomes. Time to report, time to review, length of stay, cancelled procedure, avoided appointment and documentation time can support a purchasing decision. The bridge requires evidence that saved time is releasable, redeployed or converted into additional care.
Patient outcomes should match the mechanism and observation period. Mortality, morbidity, quality of life, diagnostic delay and adverse events differ in importance and statistical power. Composite endpoints should be disaggregated. A favourable surrogate can support value only where its relationship to meaningful outcomes is credible for the intended decision.
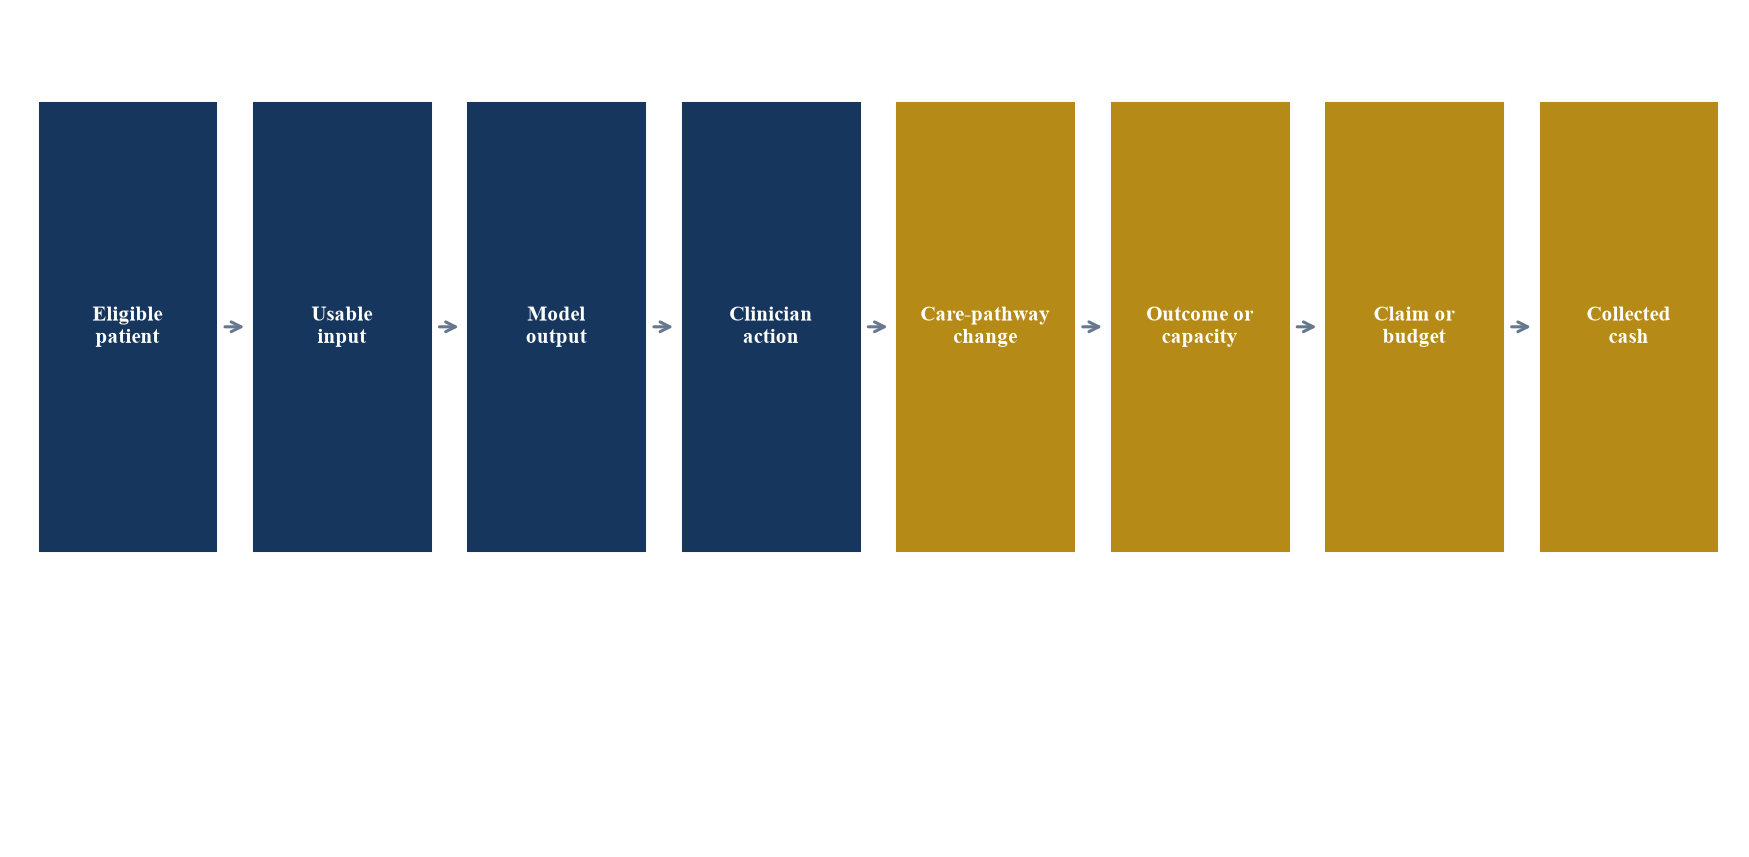
The chain requires evidence at every transition from output to collected economic value.
5. Test prospective performance and generalisability
Prospective validation should test the system in the intended workflow using data generated after the model and protocol are fixed. This reduces several forms of leakage and hindsight. It does not by itself establish generalisability to new sites, populations, devices or clinical practices.
The team should examine performance by site, time, subgroup, device, operator and data quality. Aggregate results can conceal a material weak population. Subgroup analysis should be prespecified where possible and interpreted with statistical uncertainty. Equity analysis should connect observed differences to access, error, action and outcome rather than treating demographic parity as a universal target.
Calibration matters when an output represents probability or drives thresholds. A model can rank patients effectively while producing poorly calibrated risk estimates. Threshold selection should reflect capacity and consequence. The buyer should confirm who can change a threshold, how the change is validated and whether the commercial configuration matches the study.
Abstention and failure handling affect real-world value. The model should recognise unsupported inputs where feasible, route uncertain cases and record failures. A lower headline coverage rate can be safer and more valuable than universal output if the supported population is explicit and the fallback works.
6. Separate model performance from clinical utility
A model can be accurate and clinically irrelevant. It may identify information already available to the clinician, arrive after a decision, recommend an unavailable action or add alerts to a saturated workflow. Clinical utility requires a changed decision or action that is appropriate for the patient and feasible for the service.
The buyer should measure receipt, opening, comprehension, agreement, override, action and timing. Each step forms an adoption funnel. An apparent low adoption rate can signal distrust, poor placement, inadequate training, weak relevance or appropriate rejection. Override reasons and subsequent outcomes should be captured rather than classified automatically as user error.
Human factors deserve the same diligence as the model. Interface design, alert wording, prioritisation, explanation, training, escalation and downtime procedures can alter safety and performance. The FDA and WHO emphasise transparency, user needs and human oversight across the lifecycle.[1][3] The tested system includes people, process and technology.
Capacity can reverse value. A detection tool that finds more patients may increase imaging, biopsy, specialist review, treatment or follow-up demand. If downstream capacity is unavailable, the product can create longer queues or displace higher-value care. The economic model should include the complete pathway and any bottleneck investment.
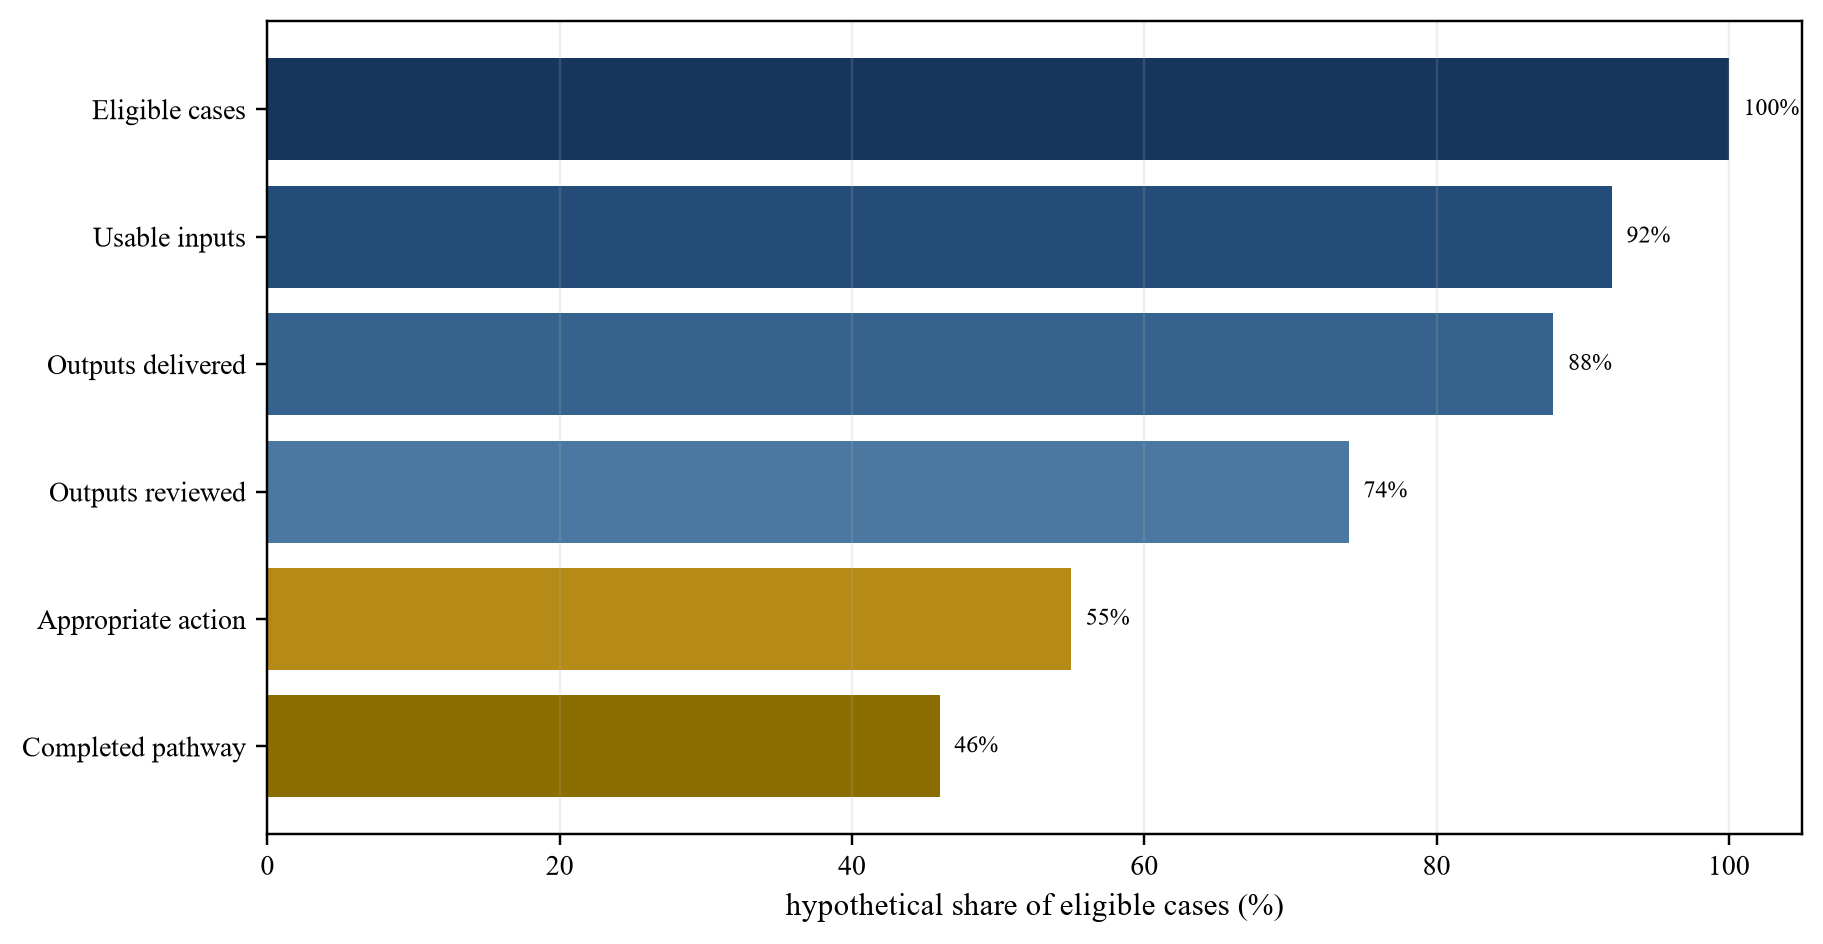
Hypothetical funnel; percentages are illustrative management assumptions and are not clinical benchmarks.
7. Map regulatory status to the commercial product
Regulatory status should be mapped to product, claim, version, user, population, input and jurisdiction. A company can operate multiple modules with different classifications or non-device functions. The buyer should identify which revenue depends on each authorisation and whether change of control, manufacturing site, quality-system responsibility or distribution arrangement affects continuity.
FDA guidance distinguishes device software functions and recommends lifecycle information for AI-enabled devices.[1][2] The European framework can involve the Medical Devices Regulation or In Vitro Diagnostic Medical Devices Regulation alongside the AI Act; the European Commission published an FAQ on this interplay in 2025.[5][6] Local analysis remains necessary for each product and market.
The technical file, quality management system, clinical evaluation, risk management, cybersecurity, usability and post-market records should align with the commercial configuration. A clean certificate does not prove that sales teams, customer contracts and deployed versions remain within the authorised claim.
Predetermined change control can support governed modification where available, but it is not a general permission to update. The buyer should map planned model, data, threshold and interface changes to the approved change protocol, verification, validation, notification and regulatory route.[2]
8. Price reimbursement and budget ownership
Regulatory authorisation permits a product to be marketed under defined conditions; it does not create reimbursement or a purchasing budget. The buyer should identify who pays, the covered service, coding, price, evidence requirement, utilisation control, contracting route and renewal decision. Payment can arise through a dedicated code, bundled payment, hospital budget, population contract, subscription or shared-savings arrangement.
The economic beneficiary can differ from the buyer. A hospital department may bear software and implementation cost while savings accrue to a payer, another department or future period. The transaction model should show the value flow and the contracting mechanism that returns an appropriate share to the vendor.
NICE's evidence standards framework connects clinical effectiveness, real-world performance, implementation, budget impact and value to commissioning decisions.[4][26] Early-use HealthTech guidance can support managed adoption with evidence generation, but conditional access should be distinguished from durable routine purchasing.[27][28]
US reimbursement can vary across setting, payer, code and service. A code does not guarantee coverage, payment amount, utilisation or vendor capture. The buyer should reconcile claims, denials, appeals, contract allowances and cash by site and payer. Provider-paid models require the same discipline around budget ownership and renewal.
| Route | Buyer | Evidence needed | Main valuation risk |
|---|---|---|---|
| dedicated reimbursement | provider or supplier | coverage, coding and claim acceptance | code without durable coverage |
| bundled payment | provider system | pathway saving and capacity | benefit absorbed by bundle |
| departmental budget | clinical or operating unit | local utility and budget impact | annual discretionary renewal |
| enterprise licence | health system | multi-site performance and governance | slow procurement and deployment |
| population contract | payer or risk-bearing provider | outcome and total-cost evidence | attribution and contract duration |
| evidence-generation access | public or provider programme | protocol and reporting | temporary adoption mistaken for scale |
Proposed map; payment rules and contracting routes require jurisdiction-specific verification.
9. Rebuild contracted, recognised and collected revenue
Clinical AI contracts can mix software licences, per-study fees, implementation, integration, support, research services and outcome-linked payments. The buyer should reconcile signed contract value, deployed sites, eligible volume, recognised revenue, invoicing, deductions and cash. A multi-year headline contract can contain termination rights, pilots, minimums that are not enforced or future modules that remain unapproved.
Contracted annual recurring revenue should be segmented by live, implementing and unstarted sites. A live site should have the intended model version in production, trained users, functioning integration, monitored activity and an accepted invoice route. Implementation revenue should remain separate from recurring licence or usage economics.
The hypothetical case reports USD 18.0 million of annual contracted revenue and USD 13.5 million of collected revenue across 28 provider sites. The gap comprises deployment timing, minimum-volume shortfall, invoice dispute and receivable delay. Every amount is hypothetical and created to demonstrate reconciliation.
Collections should be traced to bank receipt. Healthcare procurement, purchase orders, acceptance, coding, claim adjudication and budget cycles can create material delay. Bad debt, credit notes, rebates, free extensions and implementation concessions should reduce the appropriate cohort economics.
10. Build site and patient cohorts
The economic unit can be a site, department, clinician, patient, study or completed pathway. The buyer should select the unit that connects use, cost and cash. Aggregate company growth can conceal sites that never deploy, clinicians who stop using the tool or contracts whose minimum volume exceeds activity.
Site cohorts should record contract date, integration start, go-live, trained users, eligible cases, usable inputs, outputs, reviewed outputs, actions, invoices and collections. Patient cohorts should remain governed and de-identified where required. Clinical and economic analysis should use consistent denominators and version history.
Retention should distinguish contract renewal from productive use. A health system may renew during a long integration or maintain a licence at minimal activity. Gross revenue retention, net revenue retention, active-site retention and contribution retention answer different questions.
The buyer should test mature cohorts separately. Newly launched sites can benefit from vendor staff, executive attention and temporary clinical champions. Mature economics should include routine support, monitoring, retraining, integration maintenance and procurement cost.
11. Reconstruct unit economics after implementation
Revenue should be reduced by variable and directly attributable cost. Clinical data access, cloud, inference, integration interfaces, cybersecurity, annotation, quality assurance, clinical support, regulatory maintenance, post-market surveillance and customer success can be material. A software gross margin that excludes these functions can overstate contribution.
Implementation cost should include interface configuration, data mapping, validation, workflow design, information governance, training, parallel operation and remediation. Some cost is reusable; some repeats at every site. The buyer should separate platform, country, health-system and site-specific work.
The hypothetical case collects USD 13.5 million. Data, cloud and model operations cost USD 1.7 million; site integration and support cost USD 2.4 million; clinical quality, regulatory and monitoring cost USD 1.5 million; sales, procurement and partner cost USD 1.2 million; and incident, insurance and security cost USD 0.7 million. Contribution before central cost, tax and capital is USD 6.0 million.
Each amount is hypothetical. The example does not claim a representative margin. It demonstrates that prospective evidence creates value only when deployment, governance and monitoring cost remain inside the commercial model.
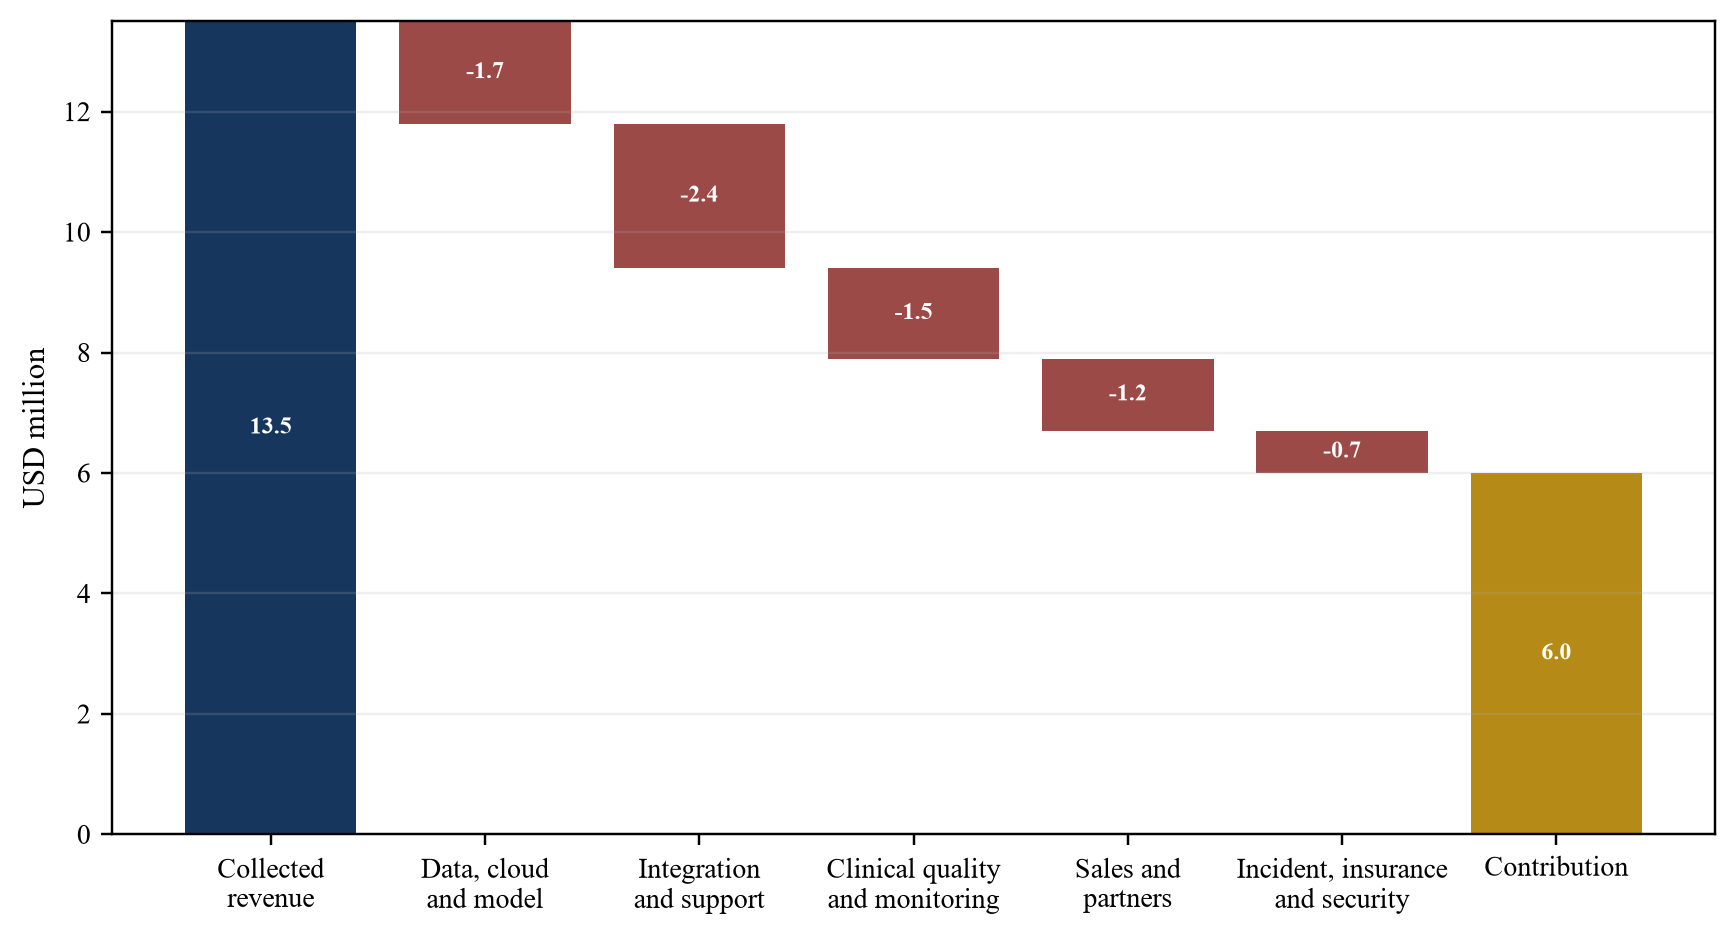
Wholly hypothetical USD millions; central cost, tax and capital remain outside the displayed contribution.
| Measure | Numerator | Denominator | Diligence use |
|---|---|---|---|
| input usability | cases processed without invalid input | eligible cases | data and integration quality |
| output review | outputs opened by intended user | delivered outputs | workflow adoption |
| appropriate action | supported actions completed | reviewed outputs | clinical utility |
| active-site retention | productive sites retained | productive sites at opening | operating durability |
| contribution per case | collected revenue less attributable cost | completed pathways | scalable economics |
| cash conversion | cash collected | recognised revenue | procurement and payer quality |
Proposed structure; financial and clinical populations should reconcile to governed source records.
12. Quantify evidence-generation cost and dilution
Additional evidence is an investment. The valuation model should include protocol design, sites, data, clinical operations, statistics, monitoring, quality, regulatory interaction and publication. It should also include time to enrol, site activation, observation and analysis. The company may require financing before the evidence event.
The financing path can dilute shareholders or add preference. A buyer pricing the company before a pivotal study should model the capital needed to reach the readout and the rights attached to that capital. Enterprise value and equity proceeds should not be conflated.
Evidence cost should be linked to the decision it can unlock. A large randomised study can be wasteful when the immediate uncertainty is integration feasibility or payer willingness. A small pilot can be insufficient when the claim requires patient-outcome evidence. The next study should target the uncertainty with the greatest expected effect on value.
Study failure should be decomposed. Recruitment delay, missing data, poor model performance, low clinician adoption, inadequate capacity and weak economics require different remediation. Some preserve the core asset; others challenge the product thesis.
The board should maintain an evidence-financing schedule. Each work package should state the decision it supports, start and completion date, cash requirement, dependency, success criterion and residual uncertainty. This makes the capital path auditable and prevents a sequence of loosely defined studies from consuming cash without changing the commercial decision.
Partnership terms can transfer evidence cost while surrendering economics or control. A strategic hospital, manufacturer or payer may fund a study in exchange for exclusivity, data rights, distribution, preferred pricing or an acquisition option. The buyer should value the funding benefit alongside the restriction on addressable market and future bargaining power.
Publication timing can differ from the valuation event. A prespecified analysis may support a regulatory or purchasing decision before peer-reviewed publication, while an attractive publication can describe an obsolete version. The diligence room should contain the governed underlying evidence, analysis code, approvals and limitations rather than treating journal acceptance as the sole quality gate.
13. Design a health-economic model
The comparator should be current practice at the purchasing setting. It should include tests, clinician time, treatment, complications, follow-up, administration and capacity. The AI pathway should include software, implementation, training, monitoring, false-positive work-up, false-negative consequence and downstream care.
Time horizon should match outcomes and payment. A hospital may focus on annual budget impact while a payer values multi-year outcomes. Discounted cost per outcome, budget impact, capacity and cash should be presented separately. A favourable cost-effectiveness result does not prove affordability or vendor revenue.
The model should distinguish resource release from theoretical time saving. Five minutes saved per case creates cash value only if staffing, overtime, outsourcing, throughput or avoided delay changes. Capacity released for additional care can be valuable even without cost reduction, but it requires demand and operational execution.
Uncertainty should be explicit. Eligible volume, adoption, prevalence, diagnostic performance, action rate, outcome effect, pathway cost, price and persistence should be varied. Structural assumptions should receive scenarios rather than narrow confidence intervals.
| Layer | Observed evidence | Modelled transition | Value test |
|---|---|---|---|
| population | eligible and usable cases | addressable volume | avoid prevalence inflation |
| performance | threshold results and uncertainty | errors by case type | price harm and work-up |
| action | reviewed outputs and overrides | changed care | separate output from utility |
| outcome | patient and capacity measures | longer-term effect | match time horizon |
| resource | staff, test and pathway use | released or added capacity | distinguish time from cash |
| payment | contract, claim and collection | renewal and price | connect benefit to vendor cash |
Proposed architecture; clinical and economic inputs require source-specific validation.
14. Value the company by evidence state
The income approach should forecast revenue and contribution by product, site cohort, reimbursement route and geography. Deployment timing, eligible volume, adoption, renewal, price and direct cost should tie to observed cohorts. Future claims or markets should be probability-weighted and separated from authorised current use.
Comparable-company multiples require normalisation. Clinical AI businesses differ in regulatory class, evidence, recurring revenue, implementation intensity, reimbursement, clinical risk, capital need and gross-versus-net revenue. Growth supported by free pilots or research grants should not be valued like collected commercial revenue.
Transaction evidence can include milestone payments, earn-outs, contingent value rights, research commitments, licence rights and retained stakes. Announced headline consideration may exceed value paid at closing. The analyst should score disclosure quality before using a transaction multiple.
Replacement cost should include lawful data access, clinical partnerships, quality systems, regulatory work, integrations, evidence, time and failure risk. Historical research expenditure does not establish economic value, while software-development cost alone understates a validated clinical asset.
Real-option analysis can value a future indication, geography or autonomous use where the company controls a credible development path. The option requires a defined investment, evidence event, timing, probability and payoff. A broad platform narrative without a specific path should remain outside central value.
The valuation model should distinguish duration from growth. Strong prospective evidence can reduce near-term adoption uncertainty without proving that advantage persists for a decade. Competing models, clinical-guideline change, data access, hospital bargaining power and model maintenance affect terminal value. Contract renewal and continued outcome evidence provide stronger duration support than technical intellectual property alone.
Capital structure also affects transaction value. Preference stacks, liquidation rights, debt, research obligations, deferred consideration and change-of-control payments should be reconciled from enterprise value to proceeds. A high headline valuation can deliver limited ordinary-shareholder value when substantial capital is required before commercial scale.
The buyer should reconcile the investment case to accounting treatment without letting purchase-price allocation determine price. Identifiable technology, customer relationships, contractual rights and trade names can have different useful lives. Goodwill can absorb expected synergy and assembled workforce, but it does not remove the need to test whether those benefits are achievable.
15. Apply an evidence discount transparently
The valuation committee should avoid one opaque clinical-risk premium. Specific deductions can address narrow populations, weak comparator, site dependence, low adoption, absent reimbursement, integration cost, version divergence, quality-system gaps, model drift and key-person dependence.
The hypothetical bridge begins with USD 120 million of enterprise value supported by current collected contribution and market assumptions. Prospective clinical utility and contracted expansion add USD 18 million and USD 12 million. Evidence transferability reduces value by USD 9 million; reimbursement and budget risk by USD 11 million; deployment and monitoring cost by USD 8 million; and integration and key-person risk by USD 5 million. The illustrative value is USD 117 million.
Every amount is hypothetical. The bridge demonstrates method and is not a valuation opinion. A transaction requires buyer returns, capital structure, tax, market evidence and specialist clinical, regulatory and reimbursement analysis.
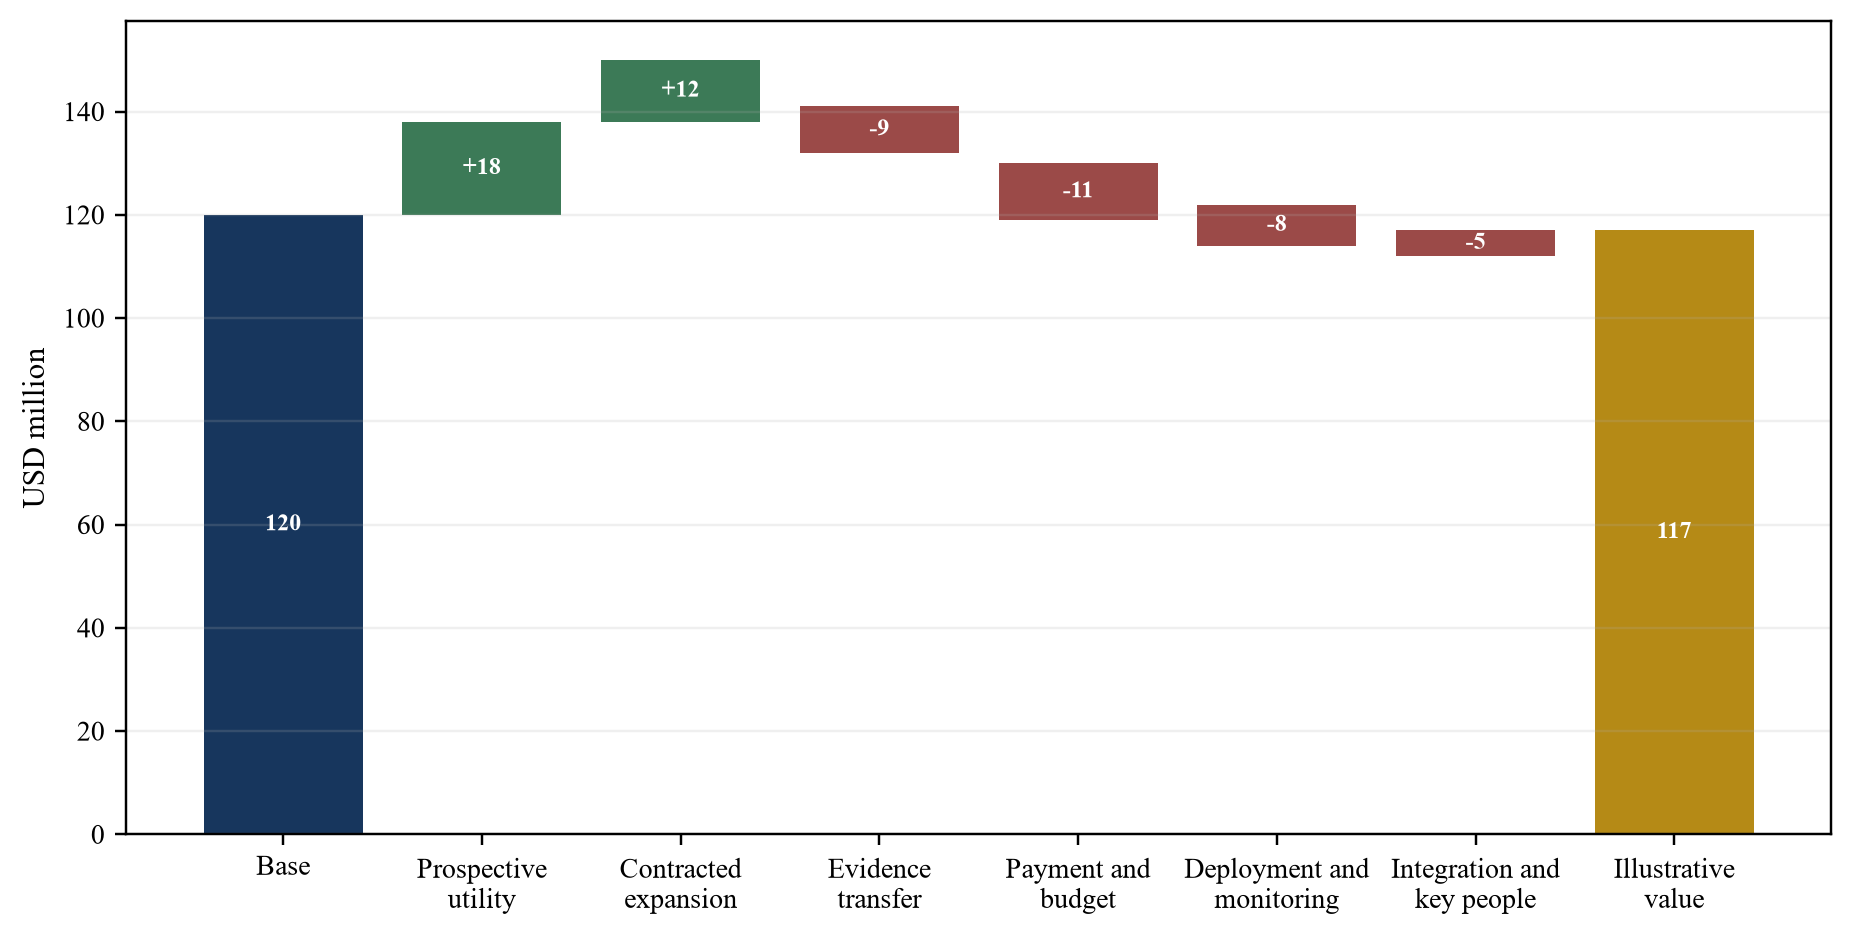
Wholly hypothetical USD millions; the bridge is methodological and is not a valuation opinion.
16. Test sensitivities and downside cases
Sensitivity should expose variables management can influence and variables controlled by the environment. Eligible volume, input usability, clinician review, action, price, deployment cost and renewal can be operationally addressed. Regulatory timing, payer coverage and market multiples may have less direct control.
Downside cases should include a failed new-site replication, reimbursement delay, material performance drift, integration outage, cybersecurity incident, regulatory restriction and loss of a clinical champion. The model should show liquidity needs and equity proceeds as well as enterprise value.
The hypothetical contribution sensitivity varies collected revenue and attributable operating cost. It excludes central cost, tax, capital and transaction financing. No cell is a forecast or benchmark.
| Collected revenue; USDm | Attributable cost USD 6.5m | USD 7.5m | USD 8.5m | USD 9.5m |
|---|---|---|---|---|
| 12.5 | 6.0 | 5.0 | 4.0 | 3.0 |
| 13.5 | 7.0 | 6.0 | 5.0 | 4.0 |
| 14.5 | 8.0 | 7.0 | 6.0 | 5.0 |
| 15.5 | 9.0 | 8.0 | 7.0 | 6.0 |
Wholly hypothetical USD millions; no cell is a forecast or market benchmark.
17. Translate evidence into transaction protections
Representations can address regulatory status, intended use, study conduct, data rights, model ownership, clinical claims, quality systems, cybersecurity, incidents, reimbursement, contracts and financial metrics. Definitions should match the evidence populations and deployed versions.
Conditions can require regulatory approval, change-of-control consent, transfer of essential data and model rights, delivery of reproducible validation, closure of a critical quality gap or execution of a material customer contract. Conditions should be reserved for matters that prevent lawful ownership or safe operation.
Interim covenants should protect the evidence base between signing and closing. Model updates, threshold changes, new claims, protocol amendments, material incidents, customer concessions and loss of clinical or regulatory personnel can alter value. Ordinary-course operation should continue within defined change control.
Escrow, indemnity and insurance should match enforceable exposure. Known evidence gaps and forward performance may receive limited warranty-insurance coverage. The buyer should model uninsured exposure, remediation cost and recovery timing.
Contingent consideration can align payment with effective authorisation, successful prospective replication, retained productive sites, reimbursement, collected contribution or a defined patient outcome. The measure needs a reproducible population, version, observation period, cost allocation, audit right and dispute route.
Milestones should reward evidence within the seller's influence while preserving safe operation. A payment tied only to regulatory submission may reward activity rather than acceptance or commercial value. A payment tied to revenue can encourage discounting, unsupported expansion or underinvestment in monitoring. Balanced milestones can combine permission, productive use, quality and collected contribution.
Operating covenants during an earn-out should define the buyer's obligations without freezing integration. The parties should agree minimum resources, commercial discretion, model change, customer allocation, pricing authority and access to evidence. An independent expert process can resolve technical or clinical disputes more effectively than a purely financial definition.
The transaction committee should map each material gap to one primary response. A weakness reflected in forecast volume should not automatically be deducted again from price and protected by a full-value earn-out. The map should show where risk is priced, retained, insured, remediated or transferred.
| Evidence gap | Price response | Protection | Release evidence |
|---|---|---|---|
| narrow prospective cohort | probability-weight expansion | milestone consideration | independent replication |
| commercial version divergence | exclude unsupported benefit | closing validation | reproducible matched performance |
| pending reimbursement | defer payment-route value | earn-out or option | coverage and collected claims |
| weak site adoption | reduce volume and margin | retention mechanism | mature productive cohorts |
| quality-system gap | funded remediation deduction | condition, escrow and covenant | tested closure |
| model-drift risk | terminal-value adjustment | monitoring and change control | stable post-market evidence |
| key clinical dependency | continuity discount | retention and transfer plan | documented repeatable governance |
Proposed matrix; legal drafting and remedies remain transaction-specific.
18. Design integration around clinical continuity
Integration can invalidate the evidence that supported value. Hosting, data mapping, interface, model version, threshold, user interface, workflow, support and quality responsibility may change. Each change should be mapped to risk assessment, verification, validation, regulatory review and customer acceptance.
The integration architecture should distinguish preserve, connect, migrate and retire. Preserve applies where the target's regulated platform and quality system remain necessary. Connect uses governed interfaces while operating systems remain separate. Migrate moves controlled cohorts after matched testing. Retire follows evidence that records, obligations and safe fallback have transferred.
Data migration should preserve provenance, consent, time, units, coding, missingness and deletion state. Normalisation can silently alter clinical meaning. Record-level reconciliation and clinically meaningful test cases should precede production use.
Model migration is a controlled clinical change. Old and new systems should process matched cases where feasible. Differences should be classified by input, preprocessing, model, threshold, interface and user response. The migration gate should require acceptable clinical, operational, security and financial results.
Customer continuity comes first. Clinicians need access, training, escalation and downtime procedures. Patients should not experience an unannounced reduction in care. Cost synergy should be released after replacement controls and operating capacity are proven.
19. Govern model change and post-market performance
The buyer should inventory every production model, rule, threshold and vendor component. Each item needs purpose, owner, version, data lineage, validation, deployment population, monitoring, fallback and retirement criteria. A catalogue limited to machine-learning artefacts misses deterministic rules and human overrides that shape outcomes.
Monitoring should connect input quality, model output, clinical action, patient outcome and incident. Statistical drift alone cannot determine clinical materiality. Stable input distributions can coexist with workflow change, and distribution shift can be harmless where performance remains appropriate.
Alert thresholds should have action limits and escalation. The team should define who investigates, how quickly, what evidence is reviewed and when deployment is restricted or rolled back. Monitoring without authority or response capacity creates documentation rather than control.
Change control should cover retraining, fine-tuning, prompt, knowledge source, threshold, input device, workflow and interface. Vendor foundation-model updates should not alter clinical behaviour silently. The approved and production configurations should be comparable and recoverable.
Post-market evidence should feed value review. Productive sites, contribution, safety, equity, reimbursement and renewal should be reassessed by version and cohort. This creates an operating valuation system rather than a one-time transaction model.
Incident governance should connect clinical safety, cybersecurity, privacy, quality, customer communication and regulatory reporting. A single event can cross all five. The target should demonstrate triage criteria, decision authority, preservation of evidence, corrective action and learning. Repeated low-severity exceptions can reveal a systemic weakness even when no single event is material.
Performance monitoring requires denominator discipline. Complaint counts, overrides or adverse events can appear stable while utilisation grows rapidly or falls. Rates should use eligible cases, processed cases, outputs or treated patients according to the question. Changes in missing cases should remain visible because excluding failed inputs can improve reported accuracy while reducing clinical coverage.
Decommissioning is part of lifecycle value. Customers need notice, record retention, data return, alternative workflow and safe rollback. The buyer should price contractual obligations and technical effort to retire obsolete versions. A controlled retirement process reduces stranded support cost and patient-safety exposure.
20. Retain clinical, regulatory and implementation capability
Clinical AI value often resides in people who understand intended use, study design, quality systems, clinical workflow, customers and regulators. The buyer should map critical roles, authority, relationships, documentation and succession. Employment title is a weak proxy for actual dependency.
Retention should focus on capability transfer. Transition plans should document model design, data decisions, thresholds, protocol history, regulatory interactions, incidents, customer configurations and reimbursement assumptions. Access and signing authority should move through controlled processes.
Clinical champions can support adoption while creating concentration risk. The buyer should identify whether evidence and customer relationships depend on a founder clinician, principal investigator or single site. Independent governance and repeatable deployment reduce that dependency.
The combined organisation needs named owners for each product, model, clinical claim, regulatory file, customer pathway and outcome. Centralisation can improve consistency while weakening local response if authority and workflow knowledge are removed too quickly.
21. Allocate synergy with evidence
Buyer-specific synergy should remain separate from seller stand-alone value. Distribution can accelerate contracting, an installed integration base can reduce deployment cost, and complementary products can increase eligible volume. Each benefit requires a named owner, budget, capacity, evidence and timing.
Cross-selling clinical AI into existing accounts requires product fit, procurement, information governance, integration, training and budget. A customer relationship is not equivalent to a purchase order. The model should apply conversion and timing supported by comparable launches.
Technology synergy should identify contracts or infrastructure that can actually be retired. Combining data sets can improve performance only where rights, consent, compatibility and clinical relevance permit use. Broader data can also reveal heterogeneity and reduce headline performance.
Headcount synergy requires a redesigned process that preserves clinical safety, quality and post-market duties. Removing implementation or clinical-support staff before workflows mature can reduce adoption and renewal. The synergy ledger should record risk and enabling investment beside every saving.
22. Execute a 180-day programme
Days one to thirty should preserve authorised versions, clinical operations, quality records, data access, customer service, monitoring and incident response. Governance, change restrictions and decision rights should be established. Revenue and collections should reconcile to contracts and activity.
Days thirty to seventy should reproduce key study results, map deployed versions, reconstruct patient and site funnels, validate rights and permissions, and identify regulatory, reimbursement and integration gaps. High-risk changes should remain restricted while evidence is incomplete.
Days seventy to one hundred and twenty should remediate priority quality, data, model, security and workflow controls. The combined firm should pilot integrations on reversible cohorts, train users, verify fallback and test economic assumptions.
Days one hundred and twenty to one hundred and eighty should season clinical and operational results, verify productive-site retention and collections, complete migration gates and release contingent value only after the agreed evidence passes.
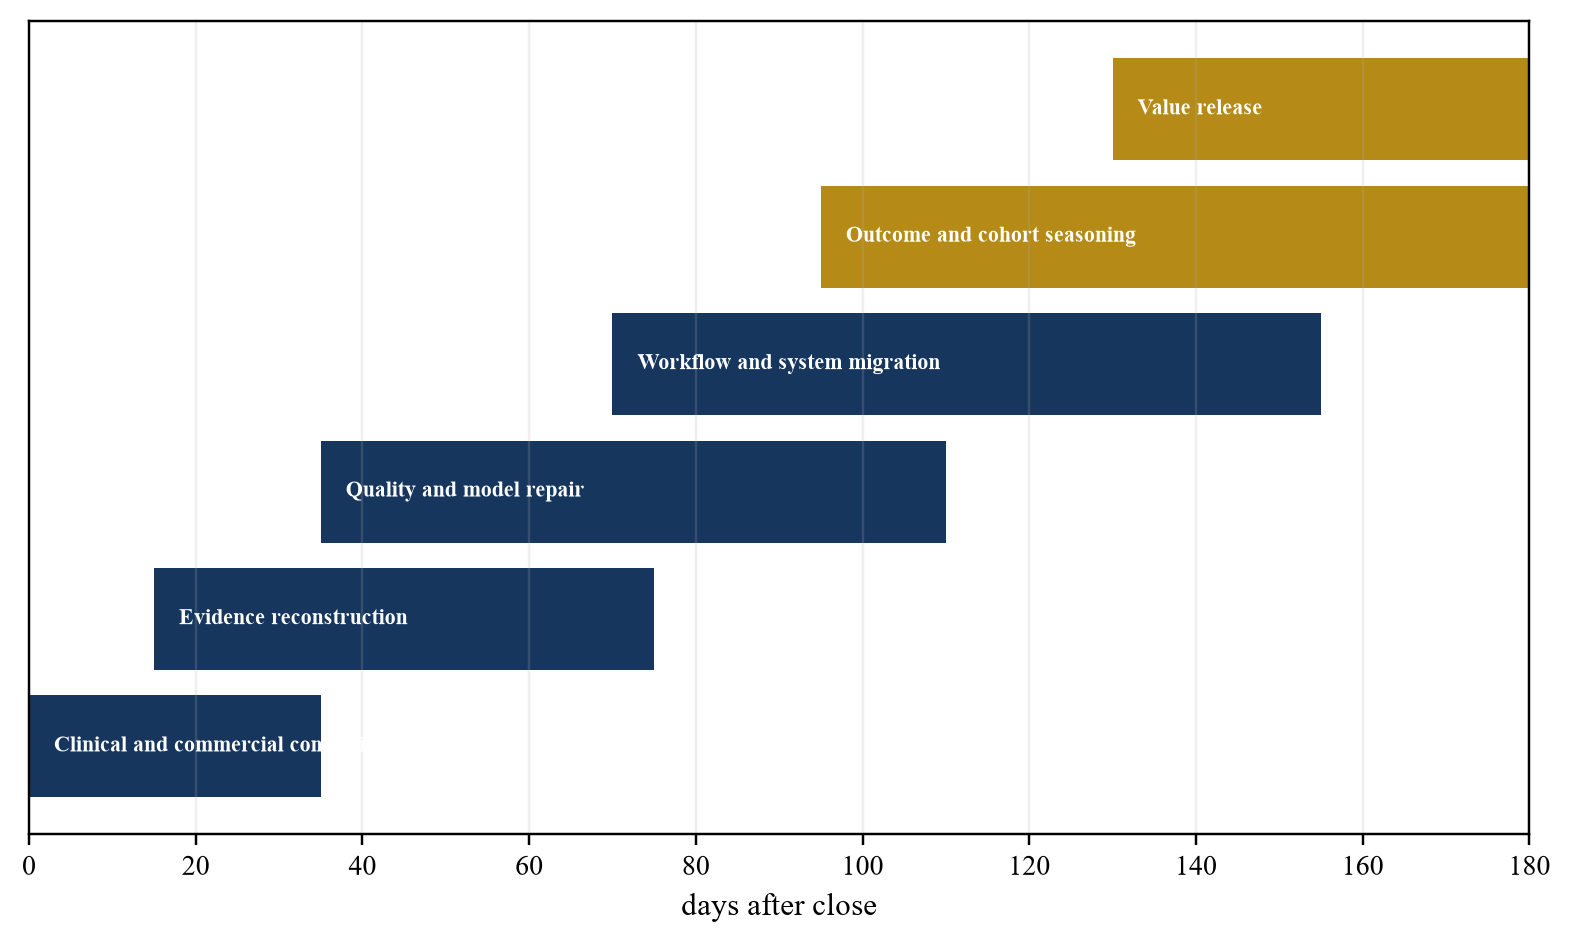
Timing should follow clinical, regulatory, reimbursement, customer and technology constraints.
23. Decision and conclusion
Prospective validation is a value event when it reduces uncertainty about a specific clinical and commercial pathway. The result should identify the model version, intended population, comparator, workflow, action and outcome. It should survive scrutiny of missing cases, site effects, subgroup performance and protocol changes.
Enterprise value requires more than a positive endpoint. The product must integrate into routine care, earn clinician action, operate within downstream capacity, satisfy regulatory and quality duties, secure budget or reimbursement, and convert productive use into collected contribution after implementation and monitoring cost.
The buyer should price each evidence layer separately. Current collected contribution and protected continuity can support central value. Prospective replication, new reimbursement, geographic expansion and autonomous use should be probability-weighted or linked to contingent consideration until evidence matures.
A premium is supportable when the commercial version reproduces prospective utility, deployed sites remain productive, payment routes are durable, quality and model governance are executable, and integration preserves clinical outcomes. Price protection, narrower scope, funded remediation or contingent value is appropriate where those conditions remain incomplete.
The central discipline is traceability. Every valuation assumption should connect to a governed patient or site population, a model version, a clinical action, an outcome, a contract, a cost and collected cash. This makes evidence maturity visible to the board and converts a promising trial into an investable, monitorable operating case.
Sources
- US Food and Drug Administration, Artificial Intelligence-Enabled Device Software Functions: Lifecycle Management and Marketing Submission Recommendations Read the primary source
- US Food and Drug Administration, Predetermined Change Control Plan for AI-Enabled Device Software Functions Read the primary source
- World Health Organization, Regulatory considerations on artificial intelligence for health Read the primary source
- National Institute for Health and Care Excellence, Evidence standards framework for digital health technologies Read the primary source
- European Commission, MDCG endorsed guidance for medical devices Read the primary source
- European Commission, MDCG 2025-6 interplay between medical-device regulation and the AI Act Read the primary source
- Medicines and Healthcare products Regulatory Agency, Software and AI as a Medical Device Change Programme Read the primary source
- US Food and Drug Administration, Health Canada and MHRA, Good Machine Learning Practice for Medical Device Development Read the primary source
- International Medical Device Regulators Forum, Software as a Medical Device Clinical Evaluation Read the primary source
- International Medical Device Regulators Forum, Machine Learning-enabled Medical Devices Key Terms and Definitions Read the primary source
- US Food and Drug Administration, Clinical Decision Support Software Read the primary source
- US Food and Drug Administration, Cybersecurity in Medical Devices Read the primary source
- US Food and Drug Administration, AI and Machine Learning Enabled Medical Devices Read the primary source
- US Food and Drug Administration, Performance Evaluation Methods for Evolving AI-Enabled Medical Devices Read the primary source
- World Health Organization, Ethics and governance of artificial intelligence for health Read the primary source
- World Health Organization, Ethics and governance of AI for health: large multi-modal models Read the primary source
- World Health Organization, Guidance on large multi-modal models for health Read the primary source
- World Health Organization, Artificial intelligence for health Read the primary source
- European Commission, Medical Device Regulation Read the primary source
- European Commission, In Vitro Diagnostic Medical Devices Regulation Read the primary source
- European Union, Artificial Intelligence Act Read the primary source
- European Union, General Data Protection Regulation Read the primary source
- European Commission, MDCG 2020-1 guidance on clinical evaluation of medical device software Read the primary source
- European Commission, MDCG 2019-11 qualification and classification of software Read the primary source
- European Medicines Agency, artificial intelligence in the medicinal product lifecycle Read the primary source
- National Institute for Health and Care Excellence, How to meet the digital-health evidence standards Read the primary source
- National Institute for Health and Care Excellence, Early-use HealthTech guidance assessments Read the primary source
- National Institute for Health and Care Excellence, Evidence generation for AI fracture detection Read the primary source
- National Institute for Health and Care Excellence, HealthTech programme methods Read the primary source
- National Institute for Health and Care Excellence, Budget impact test for digital health technologies Read the primary source
- Health Canada, Pre-market guidance for machine learning-enabled medical devices Read the primary source
- SPIRIT-AI extension, protocol guidance for clinical trials involving artificial intelligence Read the primary source
- CONSORT-AI extension, reporting clinical trials involving artificial intelligence Read the primary source
- DECIDE-AI, reporting early-stage clinical evaluation of AI decision support Read the primary source
- TRIPOD+AI statement, reporting prediction models using regression or machine learning Read the primary source
- PROBAST+AI, risk of bias assessment for prediction models Read the primary source
- EQUATOR Network, artificial intelligence reporting guidelines Read the primary source
- National Institute of Standards and Technology, AI Risk Management Framework Read the primary source
- National Institute of Standards and Technology, Cybersecurity Framework 2.0 Read the primary source
- International Organization for Standardization, ISO 13485 medical-device quality management Read the primary source
- International Organization for Standardization, ISO 14971 medical-device risk management Read the primary source
- International Organization for Standardization, ISO IEC 42001 AI management systems Read the primary source
- International Organization for Standardization, IEC 62304 medical-device software lifecycle Read the primary source
- International Organization for Standardization, IEC 62366-1 usability engineering Read the primary source
- US Centers for Medicare and Medicaid Services, Medicare Coverage Database Read the primary source
- US Centers for Medicare and Medicaid Services, coverage criteria and use of algorithms in Medicare Advantage Read the primary source
- Organisation for Economic Co-operation and Development, AI principles Read the primary source
- International Valuation Standards Council, International Valuation Standards Read the primary source
- IFRS Foundation, IFRS 3 Business Combinations Read the primary source
- IFRS Foundation, IAS 38 Intangible Assets Read the primary source
